Stopping GLP-1 Medication: What Weight Regain Studies Mean for Patients
Weight regain is common after GLP-1 drugs are stopped. Research on gradual tapering is early, so plans belong in a conversation with a clinician.
Weight regain after stopping a GLP-1 medication is common, but the evidence doesn’t show that every person will have the same experience. Studies point to a biological reason weight can return: the medication’s effects on appetite and fullness ease when treatment ends. A small case report, weight regain studies, and early real-world tapering data offer clues, but they don’t establish a reliable way to stop treatment or predict an individual outcome.
That uncertainty matters when people are weighing whether to continue. These medications can have effects beyond body weight, including blood sugar and cardiovascular measures. A decision about stopping therefore calls for a review of why the medication was prescribed, how health measures have changed, and what follow-up would look like. It’s a discussion to have with a clinician, rather than a test of willpower.
What the withdrawal studies found
In an extension of the STEP 1 study, participants who had lost weight while taking semaglutide regained about two-thirds of that weight within a year after stopping. Withdrawal research on tirzepatide found a similar pattern. These findings suggest that, for many people, the effects on weight don’t simply persist after treatment ends.
Researchers link the pattern to the body’s response to weight loss. Appetite can rise, fullness signals can weaken, and resting energy use can fall. GLP-1 medicines act on some of these processes while a person is taking them. When treatment stops, those effects lessen, and the biological pressures that can favor weight regain may become more noticeable.
These results describe groups, not a guaranteed outcome for any one person. They also don’t mean a person has failed if weight returns. Weight regulation involves biology as well as behavior, and medication can change the conditions under which eating choices are made.
There’s a preliminary sign that the way treatment ends may matter. Data from a large digital clinic program reported that patients who reduced semaglutide in stages over several weeks, alongside nutritional and behavioral support, maintained their weight loss for at least six months after stopping. Some lost a little more during the reduction period. This was real-world evidence, not proof from a controlled trial that tapering prevents regain. It’s a reason to study planned withdrawal further, not a promise of a particular result.
Why the effects can feel personal
Some patients describe a reduction in persistent thoughts about food as a sense of mental quiet. These thoughts, sometimes called “food noise,” can include repeatedly thinking about the next meal or feeling pulled toward food cues even when physical hunger isn’t present. Brain research suggests that reward and motivation circuits respond to food cues, and GLP-1 medicines may dampen some of that response.
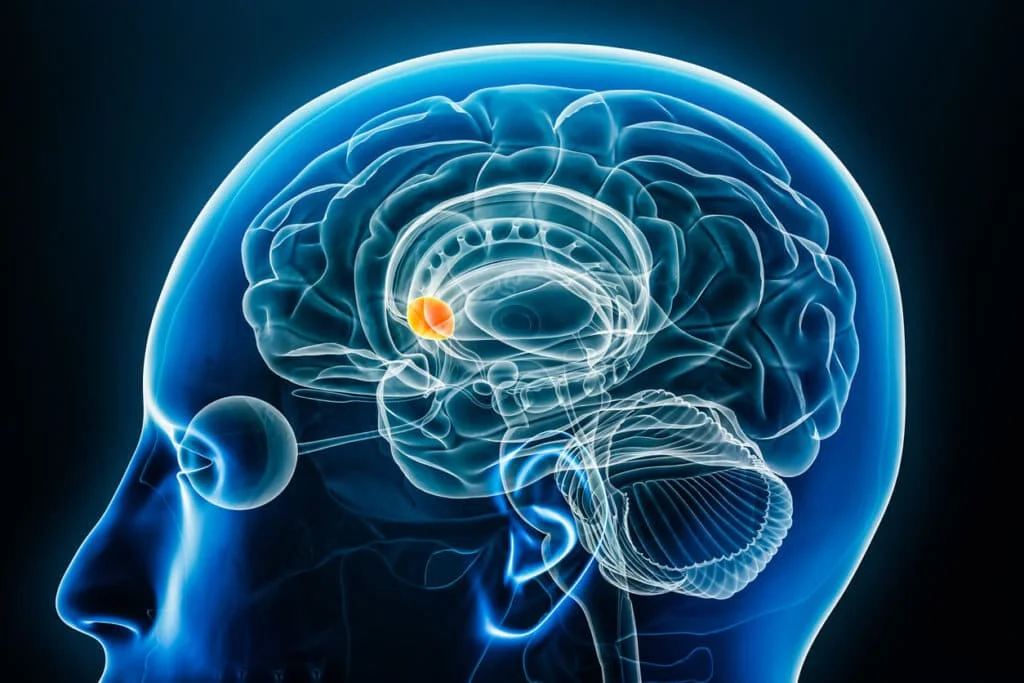
A reported case illustrates this possibility. Researchers monitored brain activity in a woman in her sixties with severe obesity and loss-of-control eating. An electrode recorded responses in the nucleus accumbens, a brain region involved in reward and motivation, as she viewed food images. After she began weekly tirzepatide, researchers observed quieter responses over the following weeks, alongside weight loss and fewer persistent food thoughts. A single case can’t establish how the medication works for everyone, but it gives a close-up view of a possible brain effect.
The broader history helps explain why these drugs affect several systems at once. Experiments in the 1960s found that drinking glucose prompted more insulin release than receiving the same glucose directly into the bloodstream. That pointed to signals from the gut. Researchers later identified hormones including GIP and GLP-1. GLP-1 helps regulate insulin release, slows stomach emptying, and acts on appetite-related brain pathways.
Natural GLP-1 is broken down quickly in the bloodstream. Research into longer-lasting versions eventually led to medicines including exenatide, semaglutide, and tirzepatide. Tirzepatide acts on both GIP and GLP-1 pathways. The drugs aren’t interchangeable in every respect, and trial results depend on the medicine, dose studied, participants, and length of follow-up.
Benefits and trade-offs vary
In major weight-management trials, average weight loss was about 15% of body weight with semaglutide over roughly 16 months. Some tirzepatide trial groups averaged more than 20%. For people with type 2 diabetes, studies have also reported reductions in A1C, a measure of average blood sugar over time. These are trial averages; individual responses differ.
Weight reduction of around 10% to 20% has been associated with improvements in blood sugar, fatty liver disease, sleep apnea, and blood pressure. Research has also found fewer major cardiovascular events in some studied populations taking semaglutide. Those results don’t mean every person taking a GLP-1 drug will experience all these benefits, or that the medicines replace other care. The patient’s health history and the reason for treatment shape what outcomes are relevant.
Digestive symptoms are among the more common side effects. Nausea, vomiting, diarrhea, and constipation can be more noticeable early in treatment or after a dose increase, and often ease as the body adjusts. Less common concerns include pancreatitis and gallbladder disease. Rapid weight loss may contribute to gallbladder problems. A thyroid cancer signal appeared in rodent research but hasn’t been replicated in human data; people with a relevant personal or family history can discuss what that means for them with a clinician.
Weight loss also includes some lean mass, which includes muscle. In clinical trials, an estimated 70% to 80% of weight lost came from fat, with the rest from lean mass. That proportion is similar to other forms of substantial weight loss. Older adults and people who are already frail may have more reason to discuss muscle strength and nutrition during treatment. A clinician or dietitian can help tailor advice about eating and activity to a person’s health and circumstances.
Planning a conversation about stopping
Rather than trying to answer “Will I need this forever?” in the abstract, patients and clinicians can review what would make a change in treatment appropriate and how to monitor it. That conversation can account for the medication’s benefits, side effects, other health conditions, and the patient’s goals. It can also cover what signs would prompt follow-up or a fresh discussion about treatment.
Some people find it useful to build routines around meals, movement, and sleep while taking medication. Those routines may support health, but they can’t guarantee that weight or appetite will remain unchanged after stopping. The original article proposes protein at meals, resistance exercise, fiber-rich foods, consistent sleep, and planned meals as areas to discuss. Individual needs vary, so people should seek advice suited to their health, rather than treating fixed targets as a universal plan.
It may also help to agree in advance on how weight and relevant health measures will be followed. A threshold for contacting the clinician or revisiting the treatment plan can make follow-up more practical. The source article mentions a 5% weight regain benchmark and changes in blood sugar as possible points to discuss; these are not universal rules for restarting medication. A clinician can help determine what measures apply to an individual.
Before considering a change, patients might take stock of whether eating patterns and activity feel manageable, whether weight has been stable, and whether relevant measures such as blood sugar, blood pressure, and blood lipids have been reviewed. Sleep and persistent food thoughts may matter to the discussion too. A checklist can organize those questions, but it can’t determine whether stopping is safe.
The source article suggests that people with stable weight and relevant lab results for at least three months might discuss a gradual taper with clinical follow-up. That is a proposed approach, not an established standard supported by definitive comparative studies. The real-world tapering findings are encouraging but preliminary, and the best approach may differ according to the medicine, the reason for taking it, and a person’s response.
The practical takeaway
GLP-1 medicines have made the biological influences on appetite and weight harder to dismiss. They can reduce hunger and persistent food thoughts for some people, and studies have found benefits for weight and other health measures. When treatment ends, those effects may fade, and weight regain is common in the studies available so far.
At the same time, the research doesn’t settle who can stop, when to do so, or whether tapering will prevent regain. The case report offers a close look at one person; withdrawal studies show group patterns; and real-world tapering data need stronger testing. Each provides a different kind of evidence, with limits.
If stopping is on your mind, bring the question to the clinician who knows your medical history. Ask how the original treatment goals are being assessed, what to monitor if treatment changes, and what support would be available if appetite, weight, or blood sugar shifts. Continuing a medicine that is helping can be appropriate care, and discussing a change can be part of that care too.






Featured image: istock.com/Varlay